
Kulwinder
Dhanowa
Life & Health Underwriting Strategy Expert
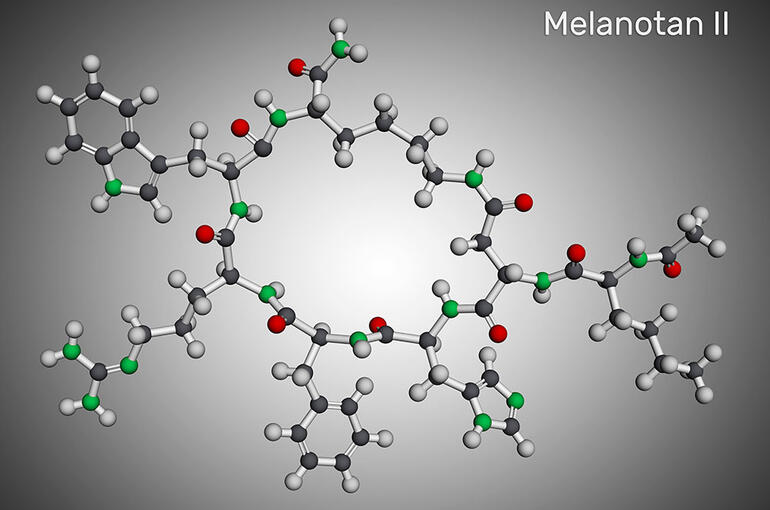
Peptide medicines – short molecule chains of amino acids – are one of the fastest growing areas of modern medicine. More than 100 peptide-based drugs have been approved around the world so far. The best known are the GLP-1 medicines for diabetes and obesity, sold under names such as Ozempic, Wegovy and Mounjaro. In the United States, nearly one in five adults say they have taken one at some point, and one in eight are taking one now.1
Because "peptide" describes a chemical structure and not a purpose, the category is very wide. It includes insulin, one of the most studied medicines in history. It also includes BPC-157, a compound that has never been tested in a controlled human trial. And there is a range of largely unapproved peptides that are making headlines currently for purportedly helping with muscle growth, recovery from injury, anti-aging, sleep, cognition and weight loss. They include BPC-157, KPV, TB-500, MOTS-c, Epitalon, Semax, Selank, Emideltide (DSIP), GHK-Cu, CJC-1295 and others. Some of them have never been assessed by any regulator. Wellness clinics, longevity programs, telehealth services and online sellers as well as grey and black market operators sell them, for instance as "research chemicals", and consumers inject them anyway.
This paper looks at what peptides are, who is using them and why, how they are obtained, what is known about their risks, and what it means for underwriting and claims. It turns out that the word "peptide" in an insurance application tells an underwriter very little on its own. The molecule, the source, the reason for use and the supervision around it tell the real story.
A peptide is a short chain of molecules called amino acids, which are the building blocks of proteins. The body naturally produces thousands of different types of peptides per day. Many act as chemical messengers that switch processes on and off. One example is insulin, a peptide that regulates blood sugar levels. Other peptides act as hormones that control growth, appetite and reproduction.
The GLP-1 medicines are a good example of a peptide drug. GLP-1 stands for glucagon-like peptide-1, a hormone that the gut naturally releases after a meal. It prompts the pancreas to release insulin, slows the emptying of the stomach and signals fullness to the brain. Drugs such as semaglutide and tirzepatide are modified copies of this peptide, designed to last a week rather than a few minutes of the natural version.
Regulators approve specific products for specific uses, made by named manufacturers under inspection. They do not approve classes of peptides. The same molecule can be sold as a licensed medicine, made up by a compounding pharmacy1, or bought as a vial of unknown content on the internet.
How the product arrives depends on where it comes from. Self-sourced peptides predominantly come as a freeze-dried powder (although nasal sprays, oral and transdermal preparations as well as topical products exist). The user mixes it with sterile water and injects it under the skin. Compounding pharmacies tend to supply a ready-mixed solution in a vial, drawn up with a syringe. Wellness and longevity clinics do both. Some administer the injection on site. Most write a prescription, teach the patient to inject and send them home with several weeks of supply. Whichever route they use, many of the people taking these products do not think of what they are doing as taking medicine.

Many peptides have relatively short biological half-lives and may be cleared from the bloodstream within hours or days. However, the duration of a peptide's presence in the body should not be confused with the duration of its biological effects. Some peptides are designed to stimulate physiological pathways that may continue to exert effects long after administration ceases, and the data is simply not available yet.
| Purpose | Examples | Approved? | What the evidence looks like |
|---|---|---|---|
| Diabetes and weight loss | Semaglutide, tirzepatide, liraglutide, dulaglutide | Yes, for type 2 diabetes and, for several products, obesity. Compounded and counterfeit copies also circulate. | Large trials measuring heart, kidney and other outcomes |
| Injury repair and recovery | BPC-157, TB-500 | No. Reviewed by the FDA's compounding committee in July 2026, with no final decision at the time of writing. | Animal studies and case reports. No controlled human trials. |
| Growth hormone release | CJC-1295, ipamorelin, sermorelin, tesamorelin | Only tesamorelin, for one HIV-related condition. | Small, short studies. Growth hormone's own effects are well known. |
| Tanning and sexual function | Melanotan II, bremelanotide (PT-141) | Only bremelanotide, in the US, for one condition. Melanotan II carries regulator warnings. | Limited. Case reports and warnings, no trials for melanotan II. |
| Longevity and anti-aging | Epitalon, MOTS-c, GHK-Cu | No. | Minimal human data. |
| Sleep, mood and cognition | Semax, selank | Only in Russia. | Very limited outside Russia. |
The user group for diabetes and weight loss is by far the largest and most diverse. GLP-1 medicines are prescribed to millions of people, mostly through normal medical channels. A 2024 US survey found that around eight in ten users got the drug from their own doctor or a specialist.2 These are mainly people with diabetes, heart disease, or obesity, taking products that have been tested in some of the largest trials in modern medicine.
The user groups of other peptides are smaller but growing and include people in chronic pain or recovering from injury, but also gym-goers, athletes, and the growing longevity and "biohacking" community. Especially the second category are generally healthy and are looking for an improvement rather than a cure: a leaner body, faster recovery, better sleep, sharper thinking or a longer life. They can also be said to be more risk-tolerant, acting without a strong underlying need, while the group of pain/surgery patients is driven by different motives and has a very different profile. And people predominantly seeking better looks (e.g. via Melanotan II for “turbo tanning”) present yet another type of users.
The route matters as much as the molecule. It decides what is known about the product, who is watching over its use, and whether there will be a record later. Four routes cover most cases.

The rules around compounding show how quickly the picture can move. In September 2023, the US Food and Drug Administration (FDA) placed 19 popular peptides, including BPC-157, on its list of substances that may present significant safety risks, which stopped pharmacies from compounding them.5 In July 2026, the FDA's own advisory committee voted – against the advice of the agency's scientists – to recommend six of those peptides for compounding after all.67 The FDA had not made a final decision as of September 2026. In Australia, the movement went the other way. From October 2024 on, pharmacies were banned from compounding GLP-1 medicines, at a time when an estimated 20,000 Australians were using compounded versions.8 In both cases the legal status changed without changes in the related medical evidence.
A product may contain the wrong sequence, a different peptide fragment, an unintended salt, too little or too much Active Pharmaceutical Ingredient (API), degradation products, synthesis residues, microbial contamination, or an undeclared pharmaceutical ingredient. The same product name does not establish analytical equivalence between batches or suppliers. Related risks are:
Even the medical record of a prescription does not ensure that the supplier did not change between refills, the storage requirements (e.g. cooling chains) were met and whether the marketed brand was identical to the dispensed product.
Injectable peptides bypass protective physiological barriers. Defective aseptic techniques, environmental contamination, unsuitable containers, inadequate refrigeration or poor beyond-use dating can lead to injection site abscesses, bloodstream infections, sepsis, meningitis etc. and have long-term health consequences. Especially for self-sourced and self-administered drugs, this risk is very high, as users need to mix the peptide powder they obtain with sterile water and draw into a syringe.
Risks increase when products are supplied in multidose vials, concentrations differ between pharmacies, instructions use non-standard “units” and telehealth patients self-inject without direct training.10 Confusion among milligrams, micrograms, millilitres and syringe units can also cause dosing and administration errors. Examples include:
Dosing errors can remain undetected for prolonged periods and lead to symptoms that are temporally delayed, making attribution difficult.
Peptides, aggregates and peptide-related impurities can provoke anti-drug antibodies. Potential consequences include loss of effect, altered clearance, delayed reactions, anaphylaxis and, in rare theoretical circumstances, cross-reactivity with an endogenous peptide. The risk depends on the molecular structure, impurity profile, route, dose, duration, and various patient factors.
Many promoted peptides lack adequately powered human trials with long follow-up. Important uncertainties include cardiovascular, hepatic, renal, endocrine, reproductive, developmental, neurological and tumour-related outcomes. Small case series cannot reliably detect uncommon or delayed harm. Few reported adverse events may simply reflect low documented exposure, incomplete follow-up, weak product identification and voluntary reporting The absence of reported harm in a small, young, self-selected group that nobody is following is not evidence of safety. Medicine has many examples, from thalidomide to the withdrawn weight-loss drugs rimonabant and lorcaserin, of harm that only became clear after years of use and formal monitoring. In addition, the use of peptides bears the potential of masking or delayed treatment of an underlying medical condition.
Peptide users might “stack” several active substances, mixing prescription drugs with others not obtained with medically supervision. Stacking can cause interactions whereby the combined impacts are different from the sum of the individual ones, unknown, and challenging to attribute. This makes it also difficult to diagnose, attribute and treat adverse outcomes. Degradation of active substances and clearance from the body depends on potential renal or hepatic impairment and can alter exposure duration and intensity of the drug.
Cost may provide additional context when assessing the likelihood, duration, and pattern of peptide use. Many approved peptide therapies involve substantial ongoing expenditure, particularly where treatment is not subsidised. For instance, monthly doses of the weight-loss peptide tirzepatide set a patient back around US$299-449 in the US, EUR200-400 in France, and A$230-460 in Australia as of mid-2026. Similarly, some non-approved peptides can be costly when used over extended periods. The financial commitment associated with ongoing use may influence treatment persistence, frequency of use, and the likelihood of future re-exposure after cessation. While cost alone is not a risk factor, it may assist in understanding whether use is likely to have been experimental, short-term, intermittent, or part of a longer-term health strategy.
| Exposure | Main risk | Quality of medical evidence |
|---|---|---|
| Approved GLP-1 medicines | The underlying condition, known side effects, stopping treatment | Large trials, ongoing safety monitoring |
| Non-prescribed opioids | Addiction, overdose, behavioural and social harm | Extensive |
| Anabolic steroids and growth hormones | Heart, liver, hormone, metabolic and psychological effects | Substantial |
| Herbal and complementary medicines | Interactions, delayed diagnosis/treatment, product quality | Variable, but decades of use |
| Unapproved peptides | Short term: Infections, toxicity, overdoses, immune responses, sepsis, willingness to take other harmful substances. Long term: cardiovascular, hepatic, renal, endocrine, reproductive, developmental, neurological and tumour-related uncertainties | Minimal |
For a better understanding of unregulated peptides, it is helpful to have a look at some examples of regulated peptides and of non-traditional drugs and their risk profile.
While GLP-1 drugs are peptides, the main difference to unregulated peptides lies in the proven effects and documented side-effects collected via large clinical trials. Uncertainties still exist around the long-term paths that users are experiencing, potentially getting on and off the medication due to complications and financial considerations. Regulated production and distribution combined with medical supervision is limiting the related risks, making them significantly safer than unregulated peptides.
The comparison with illicit injectable drugs, such as non-prescribed opioids, does not fit well. Peptides are not intoxicating and there is no evidence that they are addictive. Psychological reliance on perceived benefits may occur, particularly in fitness, bodybuilding, anti-ageing, or weight-loss settings, but this differs from classical substance dependence. Peptides also typically are taken less frequently and by a different consumer profile. Commonalities are driven by the non-regulated sourcing and route of administration (injection) and centre around the risks related to incorrect identity, purity or concentration, sterility and contamination, and dosing.
The closest match is probably anabolic steroids and growth hormones. They, too, are taken in the expectation of benefits that outweigh the risk, sourced from unapproved routes, and taken without medical guidance. But they cannot be seen as recreational and are not addictive. There is some overlap in the type of users, for the same reasons, from the same sources, and often at the same time. Again, commonalities centre around the sourcing, injection pathway, and cover risks related to incorrect identity, purity or concentration, sterility and contamination, and dosing.
Peptides share certain characteristics with herbal, naturopathic, and complementary medicines. In both cases, products may be used outside conventional medical practice, promoted for a wide range of health benefits, and may not be supported by the same level of evidence required for pharmaceutical approval.
However, there are important differences. Many herbal and complementary therapies have existed for decades and insurers have accumulated practical experience regarding their use and associated outcomes. They are produced and distributed by more traditional and better regulated channels, and the overwhelming majority is administered by routes other than injection. Commonalities are questionable effectiveness, product quality issues, and delayed diagnosis/treatment of underlying conditions.
It also pays to remember that the regulatory status of any drug may change over time and depends on the individual country. Safety requirements, prescribing, pharmacy preparation, personal importation, online sale conditions and other aspects differ between countries. Being not prescribable in some countries does not equal the fact that a substance is unsafe.
While medical science, treatments and health behaviours continue to evolve, the assessment of insurance risk must remain grounded in credible evidence and practical experience. New therapies may show promise; however, insurers require sufficient clinical literature, long-term outcome data, and claims experience to reliably assess their impact on future morbidity and mortality risk. Accordingly, underwriting practices will often evolve more gradually than medical innovation, reflecting the need for evidence-based risk management.
The use of medically approved peptide therapies prescribed and supervised by a medical practitioner should generally be assessed according to the underlying medical condition and known treatment-related risks. The use of non-approved or non-prescribed peptides warrants additional underwriting consideration due to the risks and uncertainties regarding efficacy, long-term safety, product quality, and potential future morbidity and mortality implications as detailed above, rather than due to demonstrated adverse outcomes so far.
Assessment should focus on the peptide's regulatory status, clinical context, level of medical oversight, available safety evidence, and any broader indicators of risk-taking behaviour. Insurance applicants, insureds and claimants using peptides may already have obesity, diabetes, cardiovascular disease, infertility, chronic pain or musculoskeletal injury. An adverse outcome may reflect the underlying disease, the peptide, concurrent medication, unsafe administration or an interaction. Improvement may reflect lifestyle change, intensified monitoring, placebo effects or natural recovery. Underwriting and claims conclusions should distinguish association from causation, remain evidence-based and may evolve as further clinical data, regulatory guidance, and claims experience emerge.
Despite prudence in medical underwriting, life and health insurers still might have exposure to the risks related to peptides via claims from the in-force stemming from the impacts of infections, organ injury, disability or death.
Depending on how peptides are marketed and prescribed, peptides may be viewed by insurance applicants, insureds and claimants as:
People who use non-prescribed peptides frequently do not see them as medicine, so questions about "medications", "prescriptions" or "medical treatment" miss them. Asking about "peptides" is no better. Insulin and many hormone treatments are peptides too, so the question catches the wrong people. Questions that work describe what people do: injections or supplements taken for weight, muscle, recovery, anti-aging or performance, and products bought online or from a clinic rather than a pharmacy. An assessment only based on the word "peptide" will be too harsh for the patient with diabetes on insulin and too lenient for the person injecting a research chemical.
A peptide disclosure is a lead, not a conclusion. The first question is why. A GLP-1 points to obesity, diabetes or heart disease that may not have been declared elsewhere. A recovery peptide may point to a long-standing pain or injury problem. A growth hormone product in a middle-aged man may point to a low testosterone diagnosis. The underlying condition usually matters more than the product, and it is often the thing the form has missed. In the gym and performance groups, the more important disclosure is often what else is being taken. Anabolic steroids, growth hormone and stimulants have a far better understood risk profile than the peptides themselves. A self-sourced disclosure cannot be assessed on the product name alone. The applicant may be taking the substance they believe they are taking, a different one, or nothing.
An applicant on a GLP-1 may present with a weight, blood sugar, blood pressure and cholesterol profile that is much better than it was 18 months ago, on a drug they may stop. Pre-treatment values, how long treatment has lasted, details on the history of use (ideally product and supplier chronology) and whether it is likely to continue can tell the underwriter how much of the improvement might last.11
The approved GLP-1 medicines look favorable for mortality. For income protection, disability and critical illness the picture is less clear, because the risks that matter there are infection, gastrointestinal illness, organ injury and mental health effects, which are harder to attribute and slower to resolve. The same molecule can point in different directions for different products.
Most life and health business is now assessed automatically. If the application form does not ask, no underwriter will ever see the case. The control sits in the questions and the rules, not in the judgment of an underwriter reading a file. Claims teams face the same problem from the other end. Products paid for in cash, bought online or supplied through telehealth leave no trace in medical or pharmacy records, and a hospital admission for sepsis or pancreatitis may record the complication without recording the cause.

The approved GLP-1 medicines are one of the most important advances in cardiovascular and metabolic medicine in a generation. As they spread through insured populations, mortality and morbidity experience should improve. They also open the door to prevention and engagement programs that help policyholders manage weight and heart risk.1213 That upside belongs to the approved, supervised end of the market, which is one more reason not to treat the whole class as one thing.
This article reflects the evidence available in September 2026. We would revisit it if:
Peptides are not one risk. The decisive risk variables include the exact molecule, regulatory status, source, indication, formulation, route, dose, quality controls, clinical monitoring, treatment duration and distribution scale. At one end are some of the best-evidenced medicines in current use like insulin. At the other are products of undisclosed origin whose contents cannot be verified and whose long-term effects no one has measured. The task is to tell them apart: support well-evidenced, supervised treatment and recognize its likely benefit to portfolios; treat prescribed but unapproved and compounded use as a question of managing uncertainty rather than a finding of harm; and reserve the greatest caution for products that arrive with no doctor, no pharmacist and no reliable label.
References
1 KFF Health Tracking Poll, November 2025. Poll: 1 in 8 adults say they are currently taking a GLP-1 drug for weight loss, diabetes or another condition.
2 KFF Health Tracking Poll, May 2024. Poll: 1 in 8 adults say they've taken a GLP-1 drug.
3 RACGP newsGP. TGA issues warning against unapproved peptides.
4 US Food and Drug Administration. Understanding unapproved use of approved drugs "off label".
5 US Food and Drug Administration. Certain bulk drug substances for use in compounding that may present significant safety risks.
6 US Food and Drug Administration. July 23-24, 2026 meeting of the Pharmacy Compounding Advisory Committee.
7 Health Affairs Forefront, August 2026. FDA advisory committee's vote may open a drug-compounding back door for unapproved peptides.
8 Therapeutic Goods Administration (Australia). Changes to compounding of GLP-1 receptor agonist medicines from 1 October 2024.
9 Medicines and Healthcare products Regulatory Agency (UK). Ozempic (semaglutide) and Saxenda (liraglutide): vigilance required due to potentially harmful falsified products. Drug Safety Update, November 2023.
10 US Food and Drug Administration. FDA alerts health care providers, compounders and patients of dosing errors associated with compounded injectable semaglutide products. July 2024.
11 Wilding JPH et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: the STEP 1 trial extension. Diabetes Obes Metab 2022;24:1553-1564.
12 SCOR. Weight-Loss Drugs: All That Glitters. Expert View, February 2026.
13 SCOR. Are new weight-loss drugs key to solving the obesity epidemic? Expert View, January 2024.
CONTACT
OUR EXPERTS
Kulwinder
Dhanowa
Life & Health Underwriting Strategy Expert
Irene
Merk
Emerging Risks Ambassador

Chris
Schreurs
Technical Underwriting Specialist